


Best Practice Standards for conducting PMRT reviews
Background
Drawing on eight years of experience of operating the PMRT, we have developed a series of best practice standards to support the delivery of high-quality PMRT reviews. These standards are designed to guide trusts and health boards through the PMRT review process and ensure that each review meets its primary purpose:
...to provide bereaved parents with a timely explanation of what happened with their care, why their baby died (accepting that it is not always possible to ascertain this), whether different care may have resulted in a different outcome, and whether there are any implications for their care in future pregnancies.
Meeting these standards will also support the timely achievement of the secondary purpose of reviews, enabling:
...trusts and health boards to identify and implement learning to prevent future perinatal deaths and improve future care for all mothers and babies.
A forthcoming update to the PMRT will allow individual trust and health board users to download a report from the PMRT case management screen showing current achievement against these standards for each calendar year.
Metrics for each trust and health board will be published as a separate report alongside the PMRT annual report.
Best Practice Standards
1. Notify all eligible perinatal deaths
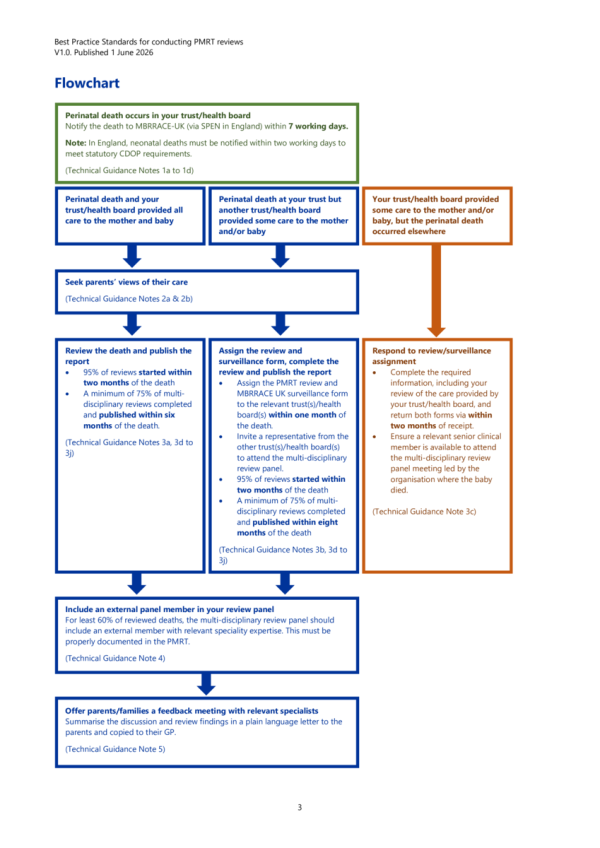
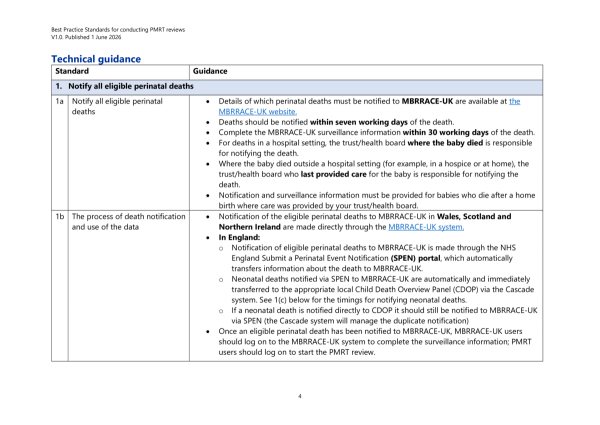
To enable the prompt start of reviews, all eligible perinatal deaths should be notified to MBRRACE-UK (via SPEN in England) within seven working days of the death.
Note: In England, neonatal deaths must be notified within two working days to meet statutory Child Death Overview Panel (CDOP) requirements.
(Technical guidance notes 1a to 1d)
2. Seek parents' views of their care
For all perinatal deaths eligible for PMRT review in your trust/health board, ensure parents are given multiple opportunities to meaningfully provide their experience of all elements of care, the impact of that care and raise any questions and comments they may have prior to the multidisciplinary review meeting.
(Technical guidance notes 2a and 2b)
3. Review the death and publish the report
Different standards apply to the review of the death and publication of the report depending on whether your trust/health board provided all or some of the care to the mother and/or baby, and where the death occurred.
(Technical guidance notes 3a to 3j)
a. The perinatal death occurred and your trust/health board provided all care to the mother and baby
A multi-disciplinary review using the PMRT should be carried out for all such deaths. Best practice standards are:
- 95% of reviews started within two months of the death.
- A minimum of 75% of multi-disciplinary reviews completed and published within six months of the death.
b. The perinatal death occurred at your trust but another trust/health board provided some care to the mother and/or baby
If care was provided by more than one organisation:
- Assign the PMRT review and MBRRACE-UK surveillance form to the relevant trust(s)/health board(s) within one month of the death.
- Invite a representative from the other trust(s)/health board(s) to attend the multi-disciplinary review panel.
Standards for multi-organisation reviews:
- 95% of reviews started within two months of the death.
- A minimum of 75% of multi-disciplinary reviews completed and published within eight months of the death.
c. Your trust/health board provided some care to the mother and/or baby, but the perinatal death occurred elsewhere
If your trust/health board provided care but the perinatal death occurred elsewhere, do not start a review. The trust where the perinatal death occurred is responsible for starting the review:
- You will be 'assigned' the review and surveillance form by the trust/health board where the baby died. (Technical Guidance Note 3c)
- Complete the required information, including your review of the care provided by your trust/health board, and return the review via the assignment function within two months of receipt.
- Ensure a relevant senior clinical member is available to attend the multi-disciplinary review panel meeting led by the organisation where the baby died.
(Technical guidance notes 3a to 3j)
4. Include an external panel member in your review panel
For at least 60% of reviewed deaths, the multi-disciplinary review panel should include an external member with relevant speciality expertise. This must be properly documented in the PMRT.
(Technical Guidance Note 4)
5. Offer parents/families a feedback meeting with relevant specialists
For all deaths reviewed, offer bereaved parents/families a meeting with an appropriate senior specialist(s) to share the review findings, discuss any implications for future care, and address any remaining questions. The review findings and discussion in this meeting should be summarised in a letter written to parents using plain language and copied to their GP.
(Technical guidance note 5)
6. Ensure that PMRT review staff undertake the PMRT online training course:
Members of staff regularly involved in the PMRT review panel in your trust/health board should complete the PMRT online training.
(Technical guidance note 6)
Download the Best Practice Standards for Conducting PMRT Reviews June 2026 Report, Flowchart and Technical Guidance Notes from below:

Best Practice Standards for Conducting PMRT Reviews June 2026 FULL REPORT
Best Practice Standards for Conducting PMRT Reviews June 2026 - FLOWCHART
Best Practice Standards for Conducting PMRT Reviews June 2026 - TECHNICAL GUIDANCE NOTES